Proposed Missouri Amendment 3 on November Ballot Would Prohibit Abortion and Gender Transition Procedures for Minors

In a June 24, 2026 ACLU article titled “Fight for Abortion Rights Has Turned to States in Years Since Landmark Reproductive Rights Ruling, Breanna Diaz, writes that “Four years ago, the Supreme Court struck down the federal right to abortion. Since then, the fight has turned to the states.”

The ACLU also maintains that “Since the Supreme Court overturned Roe v. Wade four years ago in the Dobbs v. Jackson case that ended the federal right to abortion, people across the country have felt the fallout, especially in the South and Midwest. Many have had to travel long distances to obtain abortion care in other states. Some have been denied urgently needed care at hospitals. Others have even lost their lives because of abortion bans.”

Although not perfect, I am proud that my state of Missouri now has now has Amendment 3, the “Prohibit Abortion and Gender Transition Procedures for Minors Amendment“ is on the ballot in Missouri as a legislatively referred constitutional amendment on November 3, 2026.[1]

According to Ballotpedia:


A “yes” vote supports amending the Missouri Constitution to:
:repeal the constitutional right to reproductive freedom, which voters ratified in 2024 and prohibit abortions except in cases of “medical emergency, fetal anomaly, rape, or incest,” and permit abortions in cases of rape or incest only through 12 weeks of gestation; 
prohibit gender transition surgeries for minors, as well as the prescription or administration of cross-sex hormones or puberty-blocking drugs to minors, with an exception for treatments “unrelated to the purpose of a gender transition;” and make other changes.
A “no” vote opposes amending the Missouri Constitution, keeping the existing constitutional right to reproductive freedom, and not adding provisions that prohibit abortion and gender transition surgeries and procedures.

Ballotpedia states that:

“This amendment would repeal Amendment 3, which was passed by voters in 2024. It amended the state constitution, providing for the fundamental right to reproductive freedom, including abortion.

The amendment would then add a new section that would prohibit abortion, except in cases of medical emergency, fetal anomaly, rape, or incest. For cases of rape and incest, the abortion could only be performed before 12 weeks. It would prohibit abortions based on a fetal disability diagnosis, except in cases of fetal anomaly. It would require parental or guardian consent for minors seeking an abortion and prohibit fetal organ harvesting. The amendment would also provide for the ability of a woman to access healthcare in cases of miscarriage and ectopic pregnancy.[1]

State Sen. Brad Hudson (R-33), who supports HJR 73, said, “From constituents and individuals that I’ve been talking to about this issue, they want another opportunity to weigh in on this. They don’t feel like that they were given an option in Amendment 3 that accurately reflects who they are and where they are on the life issue.”[2]

Margot Riphagen, president and CEO of Planned Parenthood Great Rivers Action, who opposes the measure, said, “The majority of Missourians want to make their own decisions about health care without interference from prying politicians … We will not stand for more political games at the expense of the thousands of patients in Missouri who could finally access care they need without crossing state lines. Missouri voters will once again send a clear message that enough is enough.”[3]

Abortion is currently legal in Missouri up to the point of fetal viability, which is defined in Missouri law as “that stage of fetal development when the life of the unborn child may be continued indefinitely outside the womb by natural or artificial life-supportive systems.”[4]

and:

“Missouri was one of 14 states that placed a constitutional amendment on a ballot to amend the state constitution to provide for the right to an abortion. The first three states to pass these amendments were California, Michigan, and Vermont in 2022, the same year that Roe v. Wade was overturned following the Dobbs v. Jackson Women’s Health Organization U.S. Supreme Court decision. Out of the 14 states, voters passed right-to-abortion amendments in 11 of them, and rejected amendments in three — Florida, Nebraska, and South Dakota. After 2022, voters in one state — Nebraska — approved a measure to limit the timeframe during which an abortion can be performed.

With Missouri’s Amendment 3, this will be the first time voters will decide to repeal a right-to-abortion amendment.”

“The ballot measure would repeal Section 36 of Article I of the Missouri Constitution, and add a new section, Section 36a. The following underlined text would be added and struck-through text would be deleted”:

“Section 36(a).1. The state’s duty to protect public health and welfare includes protecting the integrity and ethics of the medical profession. The state’s interest in regulating the practice of medicine is even greater in areas of medical and scientific uncertainty or in areas that raise grave moral and ethical concerns, including abortion and gender transition procedures.

2. An abortion may be performed or induced upon a woman in cases of medical emergency, fetal anomaly, rape, or incest. In the case of abortions performed or induced in cases of rape or incest, the abortion may be performed or induced no later than twelve weeks gestational age of the unborn child.

3. The general assembly may enact laws that regulate the provision of abortions, abortion facilities, and abortion providers to ensure the health and safety of the pregnant mother. These laws shall include, but not be limited to, laws requiring physicians providing abortion care to have admitting privileges at a nearby hospital; laws requiring facilities where abortions are performed or induced to be licensed and inspected for clean and safe conditions and adequate instruments to treat any emergencies arising from an abortion procedure; laws requiring physicians to perform a sufficient examination of the woman to determine the unborn child’s gestational age and any preexisting medical conditions that may influence the procedure; and laws requiring ultrasounds to be performed only by physicians or licensed medical technicians.

4. No abortion shall be performed or induced upon a woman based on a prenatal diagnosis, test, or screening indicating a disability in an unborn child, except in cases of a fetal anomaly.

5. No public funds shall be expended for the purpose of performing, inducing, or otherwise assisting any abortion, except in cases of medical emergency, rape, or incest, as otherwise authorized by law.

6. Except in cases of a medical emergency in which consent cannot be obtained, no abortion shall be performed or induced upon a woman without her voluntary and informed consent, given freely and without coercion. In the case of a minor under the age of eighteen years who is not emancipated, no person shall knowingly perform or induce an abortion, except in cases of a medical emergency in which consent cannot be obtained, unless the attending physician has obtained:

(1) the written consent of the minor and a parent or legal guardian; and(2) documentation of the consent is retained in the minor’s medical record. Licensed medical physicians shall be required to provide women with medically accurate information. The general assembly may enact laws to provide for the right of a minor to consent to an abortion as granted by a court order.

7. Fetal organ harvesting after an abortion is not permitted under any circumstances.

8. A woman’s ability to access health care in cases of miscarriages, ectopic pregnancies, and other medical emergencies shall not be infringed by the state.

9. No gender transition surgeries shall be knowingly performed on children under eighteen years of age, and no cross-sex hormones or puberty-blocking drugs shall be knowingly prescribed or administered for the purpose of gender transition to children under eighteen years of age. The provisions of this section shall not apply to the use of such surgeries, drugs, or hormones to treat children born with a medically verifiable disorder of sex development or to treat any infection, injury, disease, or disorder unrelated to the purpose of a gender transition.

10. Any action challenging the validity of any state law relating to reproductive health care shall be brought in the Circuit Court of Cole County, Missouri. If a pleading, written motion, or other paper drawing into question the constitutionality of a state statute does not include the state, one of its agencies, or one of its officers or employees in an official capacity, the party bringing the action shall file a notice of constitutional question and serve it on the attorney general and the attorney general shall have the right to intervene in the litigation.

11. The general assembly shall have the authority to enact laws to carry out the provisions of this section.

12. As used in this section, the following terms mean:

(1) “Cross-sex hormones”, testosterone, estrogen, or other androgens given to an individual in amounts that are greater or more potent than would normally occur naturally in a healthy individual of the same age and sex;

(2) “Fetal anomaly”, a structural or functional abnormality in the unborn child’s gestational development that would make life outside the womb impossible;

(3) “Fetal organ harvesting”, collection of fetal tissue, organs, or fluids, including any biological material, for the purpose of selling or collecting for scientific purposes, but shall not include the utilization of fetal tissue, organs, or fluids to determine the cause or causes of any anomaly, illness, death, or genetic condition of the unborn child, the paternity of the unborn child, or for law enforcement purposes;

(4) “Gender transition surgery”, a surgical procedure performed for the purpose of assisting an individual with identifying with and living as a gender different from his or her biological sex;

(5) “Medical emergency”, a condition that, based on reasonable medical judgment, so complicates the medical condition of a pregnant woman as to necessitate the immediate termination of her pregnancy to avert the death of the pregnant woman or for which a delay will create a serious risk of substantial and irreversible physical impairment of a major bodily function of the pregnant woman. A medical emergency shall include, but not be limited to, an ectopic pregnancy at any point following the diagnosis of such and treatment for a miscarriage;

(6) “Puberty-blocking drugs”, gonadotropin-releasing hormone analogues or other synthetic drugs used to stop luteinizing hormone secretion and follicle stimulating hormone secretion, synthetic antiandrogen drugs to block the androgen receptor, or any other drug used to delay or suppress pubertal development in children for the purpose of assisting an individual with a gender transition;(7) “Reasonable medical judgment”, a medical judgment that would be made by a reasonably prudent physician, knowledgeable about the case and the treatment possibilities with respect to the medical conditions involved.

13. All provisions of this section are severable. If any provision of this section is found by a court of competent jurisdiction to be unconstitutional or unconstitutionally enacted, the remaining provisions of this section shall be and remain valid.

It is expected that the vote will be close.
Share this:

California is Suing Christian nonprofits that Help Women Save Their Unborn Babies

In a disturbing op-ed in the July 30, 2026 edition of the Wall Street Journal titled “California’s Case Against Second Chances,” Archbishop Salvatore of San Francisco and Bishop Michael C. Barber of Oakland write that “The State is suing Christian non-profits that help women save their unborn babies.”

The Bishops write:

“Elizabeth Barrett, a young college dropout in Southern California, swallowed a pill the local abortion clinic had given her—and then, almost immediately after, changed her mind. An online search for advice on how to undo the chemical abortion led her to Heartbeat International, a Christian nonprofit that refers women to licensed doctors for treatment. It worked. Ms. Barrett is the mother of a healthy girl.

The state of California wants to be sure that such things never happen again. In an extraordinary case now unfolding at trial in state court in Oakland, California’s attorney general seeks an injunction and up to $20 million in fines against Heartbeat International and another small pro-life Christian nonprofit, RealOptions. Their offense is telling women who regret swallowing the abortion pill that there is a medical treatment that can sometimes save their babies.

Consumer fraud, the prosecutors are calling it. Legal scholars call it an abuse of power. “This novel use of California’s commercial-fraud statute seems designed to intimidate nonprofit organizations that—with no hope of commercial gain—seek to educate the public about services that are lawful but contrary to the ideological preferences of the government,” says Michael McConnell, a professor who teaches free-speech law at Stanford.

California isn’t alone in attacking these Christian groups. New York’s Attorney General Letitia James has filed a similar lawsuit against Heartbeat International and other pregnancy centers. The Thomas More Society, a Catholic public-interest law firm, is pursuing separate federal cases challenging the constitutionality of these prosecutions in federal courts.

California’s attorney general has found no evidence that any woman has complained of harm by the defendants. That didn’t dissuade the state, which is marshaling its taxpayer-funded resources to shut these ministries down.

The state argues that because the nonprofits raise money from donors, they are engaged in commercial speech. If the government wins, doctors may still prescribe the medication, but no nonprofit can tell women the treatment exists—a novel legal theory that would vastly expand lawfare against those who hold views with which the government disagrees.

One wonders whether the pro-abortion lobby has really thought this through. The prosecution’s theory “would expose any nonprofit in America” to “the same government overreach,” Paul Jonna, an attorney from the Thomas More Society, said in a news release. Don’t they worry that some future state attorney general in Mississippi might use similar tactics to go after Planned Parenthood?

Reading the depositions of these women is a painful experience. To be a Catholic priest these days, as we both are, is to have heard many similar stories of women who felt pressured to have an abortion they didn’t want.

Everyone should oppose this. But these women especially need support from the religious—those who hold that creation in God’s image means life is endowed with a dignity that can’t be trampled by a government determined to punish those who oppose unquestioned abortion.

Consider just the case of Ms. Barrett. In 2023, she was struggling financially, and she and her live-in boyfriend were experiencing increasing strain in their relationship. When she learned she was pregnant, “I panicked at the thought of spending 18 years in family court,” Ms. Barrett testified. She “struggled to imagine where I would be able to find funds to cover child-care costs.”

At the clinic, she told staff she was scared and thought she might want to keep her baby, hoping to talk through her options. “I was a huge supporter and donor to Planned Parenthood at the time,” she said. “I thought for sure that staff at the clinic would help me out.” Instead they urged her to take the abortion pill that day and warned that if she delayed, she might not be able to get another appointment. “With that scheduling pressure and overwhelmed by misgivings about getting the abortion—what if I wanted to proceed but couldn’t later?—I took the first of two pills for a chemical abortion.”

But before she left the clinic, her boyfriend texted her saying he wanted to keep the baby and raise their child together. That changed everything. So began a frantic search for anything to stop the abortion: “I was desperate, borderline hysterical, and willing to try just about anything.” Ms. Barrett found Heartbeat International online. Within an hour, she had a clinic appointment with a licensed California doctor to reverse her abortion pill. She’s a mother today thanks to this Christian nonprofit and its donors.

California v. Heartbeat International and RealOptions is a rare case that should bring together both sides of the abortion debate. In particular, it tests the souls of those who claim the platform of “pro-choice.” What kind of people see a pregnant woman who wants to reverse the effects of an abortion pill and think, “Let’s punish the nonprofits that informed her she has a choice”?

Are they really pro-choice, or do they just like killing?

Archbishop Cordileone is archbishop of San Francisco. Bishop Barber is bishop of Oakland.“

CONCLUSION

It is not just abortion clinics, it is also about teleheath abortions.

As I wrote June 4, 2026,

New Lozier Study Shows Chemical Abortions Are Largely Unregulated

 nancyvalko abortion, chemical abortions, education, law, medical, medical abortion, medical ethics, Planned Parenthood, safeguards

As a new June 4, 2026, National Right to Life article by Michael New titled “New Lozier Study Shows Chemical Abortions Are Largely Unregulated” just reported:

“Last week, the Charlotte Lozier Institute released a study by research associate Mia Steupert showing that organizations selling chemical abortion pills online are largely unregulated. Specifically, these organizations often fail to comply with existing laws, FDA regulations, and basic health and safety standards. The study considered entities that provide telehealth abortions through the formal U.S. health-care system. The study also considered overseas and online entities that sell abortion pills.

Here are some of the specifics. The Lozier study identified 80 organizations that provide telehealth abortions through the formal U.S. health-care system. Thirty-eight of these organizations are online only, and 42 are hybrid brick-and-mortar and online facilities. Again, these facilities are technically subject to FDA regulations. The study, however, provides strong evidence that these facilities frequently violate FDA policies, states’ pro-life laws, and basic health standards:

  • Only 15 of 80 report they will adhere to FDA rules and not ship abortion pills to pregnant women after 70 days gestation.
  • 43 of the 80 either had no age requirement for the woman obtaining abortion pills or did not publish this information. This would put them in violation of state parental involvement laws.
  • Only 39 of the 80 formally required women to take part in a video call to discuss their eligibility for taking abortion drugs.
  • Only 9 of 80 require that all women submit a form of identification before obtaining abortion pills. One additional organization required a form of identification only from women living in certain states.
  • Only 16 of 80 require a virtual follow-up after the abortion has taken place.“

Since the Supreme Court’s Dobbs decision, unregulated telehealth abortions have posed a serious challenge to the pro-life movement. These telehealth abortions undermine and weaken many of the strong state-level pro-life laws that have been enacted post-Dobbs. This new Lozier study highlights the extent to which chemical abortions are largely unregulated, posing serious public health concerns. The study also details ongoing litigation where women unknowingly took chemical abortion pills because their partners wanted their pregnancies terminated. Had appropriate regulations and safeguards been in effect, these women and their preborn children would have been protected.

The Lozier study identifies several policy tools that could be used to ban or limit telehealth abortions. The FDA could restore the rules that existed before the COVID-19 pandemic and require women obtaining chemical abortions to have an in-person meeting with a health-care professional. Multiple lawsuits are being filed by various state attorneys general, arguing that the new rules violate the FDA’s Administrative Procedures Act. Finally, the Comstock Act, which prevents abortifacients from being sent through the mail, could be enforced.

This important Lozier study demonstrates that stopping telehealth abortions should remain a top priority for pro-lifers.

This appeared at National Review Online and is posted with the author’s permission.“

Share this:

s

s

Abortion pills: Where are they legal and illegal?

In a January 8, 2025, article by the Catholic News Agency titled Abortion pills: Where are they legal and illegal?, author Jonah McKeown writes:

“As states continue to legislate on abortion in the post-Roe v. Wade landscape, a major point of contention as a new presidential administration takes office is the two-drug medication abortion regimen, commonly referred to as the abortion pill.

Abortions done via medication, also called chemical abortions, currently account for about half of the abortions that are done in the United States every year. However, many states restrict the use of abortion pills, specifically the first drug in the two-drug regimen, mifepristone. (Emphasis added)”

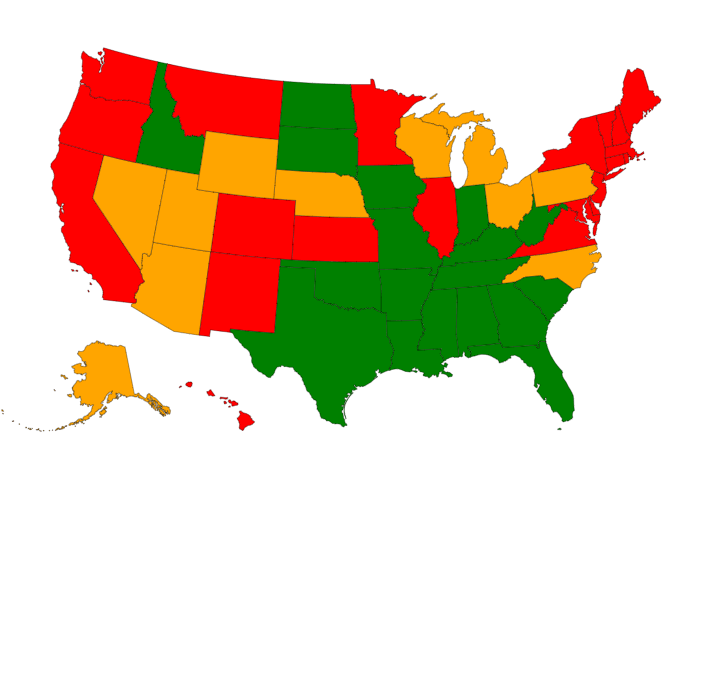
Take a look at the map below to see where abortion pills are legal, and where they aren’t:

Green is illegal, yellow is limited, and red is legal (go to Abortion pills: Where are they legal and illegal? to click on each state’s specific law)

As the author states:

“At the federal level, mifepristone is approved to abort an unborn child up to 10 weeks’ gestation, having been first approved for such use in 2000. 

The drug kills the child by blocking the hormone progesterone, which cuts off the child’s supply of oxygen and nutrients. A second pill, misoprostol, is taken between 24 to 48 hours after mifepristone to induce contractions and expel the child’s body.

Several states, most of which have some pro-life laws in place, have also passed restrictions on abortion pills designed to protect women, including requirements that only physicians may dispense them. These states include Alaska, Arizona, Florida, Georgia, Iowa, Michigan, Nebraska, Nevada, North Carolina, Ohio, Pennsylvania, South Carolina, and Utah. (Emphasis added)”

and

“A large number of states — most of them concentrated in a contiguous cluster in the South and Midwest — ban abortion in most cases but provide exceptions in cases where the life of the mother is at risk or in cases of rape, incest, or fetal anomaly. In these states, access to abortion pills is likely to be very limited or prohibited entirely. 

States with total bans on abortion pills include Alabama, Arkansas, Idaho, Indiana, Kentucky, Louisiana, Mississippi, Missouri, North Dakota, Oklahoma, South Dakota, Tennessee, and Texas. “

However, as Mr. McKeown. also writes,

” just because these states have bans on abortion pills in place does not mean the drugs are not accessible; women in those states can still receive them in the mail. Under then-President Donald Trump during the COVID-19 pandemic in 2020, the FDA was given the ability to distribute the drug via mail. The administration of President Joe Biden eventually solidified the practice as a norm in 2023. (Emphasis added)

A group of state attorneys general, led by Missouri, is currently suing the Food and Drug Administration (FDA) over its deregulation of the drug, arguing that abortion drugs have been “flooding states like Missouri and Idaho [where abortion is otherwise regulated] and sending women in these states to the emergency room.”

In addition, Texas Attorney General Ken Paxton recently filed a lawsuit against an abortionist in New York, alleging that she illegally provided abortion drugs to a woman in Texas, which killed the unborn child and caused serious health complications for the mother.”

Sadly, as Mr. McKeown writes:

President-elect Trump has committed to keeping abortion pills accessible during his second term — a major disappointment for pro-life advocates, who have urged Trump to use the FDA’s power to enforce a Comstock Act prohibition on the delivery of “obscene” and “vile” products through the mail, which includes the delivery of anything designed to produce an abortion.”

CONCLUSION

As I wrote in my June 16, 2024 blog “The Supreme Court Rejects Challenge by Pro-life Doctors on Abortion Pill“:

“As Life News reported on June 13, 2024:

“The Supreme Court on Thursday rejected a challenge to the abortion pill mifepristone, meaning the abortion drug will be widely available to continue killing babies and injuring doctors nationwide.

The 9-0 decision says the pro-life doctors who brought the case do not have standing – they were not injured, and so the court does not intervene. That’s even though they sued on behalf of women who were injured by the abortion drug by the thousands – including women who have been killed.” (Emphasis added)”

I have a personal interest in this because I had an unwed daughter who became pregnant and started bleeding without telling me because of embarrassment.

She went to a local ER, where the doctors said she was just having a miscarriage and sent her home.

When the pain and bleeding increased, she called me. I took her back to the ER to demand an ultrasound.

As I suspected as a nurse, her pregnancy was ectopic and emergency surgery was performed.

Afterward, the surgeon showed me the picture he had taken (unasked) during the surgery to remove the then-deceased first-trimester baby, my grandchild. The picture was personally so sad to see but I was comforted that the surgeon cared enough to take a picture of this tiny person and show respect.

We need more respect and help for women with an unexpected pregnancy and their babies than a pill without medical safeguards!”

Related

“Safer Than Tylenol” is Deliberate Medical Abortion Disinformation February 26, 2023

Planned Parenthood Sues Kansas to Challenge a New State Law Requiring Abortion Reversal Information to be Provided Before Abortion June 12, 2023

How to Bury Your Baby After a Miscarriage Today

10 years ago, I wrote my blog “How to Bury Your Baby After a Miscarriage” after my miscarriage:

“In 1983, my daughter Karen, who had Down Syndrome, died at 5 1/2 months from a complication of pneumonia just before her open heart surgery. In 1984, we suffered a miscarriage at 10-12 weeks.

My 7-year-old son and 5-year-old daughter were devastated and asked what the name was. Since the doctors could not determine the sex of the baby, I had each of my children select a boy’s or girl’s name. Naming the baby Jeff Candy helped make my children feel better but then they questioned why Jeff Candy did not have a funeral like their sister Karen. Good question!

I brought this up to my mentor Fr. Joe Naumann (now archbishop of Kansas City) when he headed the St. Louis Archdiocesan Pro-Life Committee and the next thing I knew, I wound up on a committee. Now we have “The Order for the Naming and Commendation for an Infant Who Died Before Birth” (copyright 1989)
.
I am so proud of the results of my children’s long-ago question and I am so happy to see the long-term results in this article, which should be shared with everyone, especially if they are Catholic. Here is an excerpt:

How to Bury Your Baby After a Miscarriage

by JoAnna Wahlund • June 10, AD2015

“The loss of a child is a nightmare for every parent. In the first few hours and days of grief and shock, it’s hard to know what to do. It’s especially hard when the loss occurs in early pregnancy, since our culture isn’t accustomed to treating unborn babies as human beings — and this happens even in pro-life circles.

If you are reading this article because you recently lost a baby via miscarriage, there are three things I want you to know:

1. I am so sorry for the loss of your baby.

2. You have the right to bury your baby.

3. If you did not bury your baby, do not not feel ashamed or guilty. We can only do our best in the circumstances we’re in according to the knowledge that we have.”

A MISCARRIAGE AND FUNERAL TODAY

Recently, I was invited to an ultrasound of a close relative.

“Anne” (not her real name) was so excited about her third pregnancy, and since I was a nurse, she thought I might be able to discern the sex of the baby.

I held her hand as the ultrasound began, but tragically, there was no heartbeat.

A second ultrasound showed the same result, and we both cried as a D&C was scheduled to remove the baby.

I had told Anne about the Naming and Commendation Ceremony and she requested the baby’s remains. The hospital was very respectful and put the remains in a small white box.

We met with her pastor, who not only agreed to bury the baby in the church’s graveyard with a short ceremony, but also to have a stone placed!

What a blessing!

.

The Supreme Court Rejects Challenge by Pro-life Doctors on Abortion Pill

As Life News reported on June 13, 2024:

“The Supreme Court on Thursday rejected a challenge to the abortion pill mifepristone, meaning the abortion drug will be widely available to continue killing babies and injuring doctors nationwide.

The 9-0 decision says the pro-life doctors who brought the case do not have standing – they were not injured, and so the court does not intervene. That’s even though they sued on behalf of women who were injured by the abortion drug by the thousands – including women who have been killed.” (Emphasis added)

The US Supreme Court decision acknowledged that the Mifeprex pill was approved in 2000 but also that:

“FDA placed additional restrictions on the drug’s use and distribution, for example requiring doctors to prescribe or to supervise prescription of Mifeprex, and requiring patients to have three in-person visits with
the doctor to receive the drug.
” (Emphasis added)

The Cout also acknowledges that the restrictions were relaxed further by the FDA (Federal Drug Administration) when:

“In 2021, the FDA announced that it would no longer enforce the initial in-person visit requirement. Four pro-life medical associations and several individual doctors moved for a preliminary injunction that would require the FDA either to rescind
approval of mifepristone or to rescind the FDA’s 2016 and 2021 regulatory actions. Danco Laboratories, which sponsors Mifeprex, intervened to defend FDA’s actions.”

Now as the Wall Street Journal reports:

“Twenty-six states and D.C. allow telehealth for medication abortion. The remaining states have restrictions that supersede federal guidance: 14 ban abortion throughout pregnancy, and the remaining 10 have various combinations of in-person requirements, such as mandatory ultrasounds and visits to doctors and counselors.” (Emphasis added)

WHAT COULD GO WRONG?

As Dr. Christina Francis, an Ob-Gyn doctor herself, wrote in a May 2021 article titled “The government’s abortion pill policy puts mothers’ lives at risk”:

“One of the most significant reasons why an in-person visit has been required is for proper medical oversight as well as a physical exam and ultrasound. These visits are meant to accurately assess the gestational age of a woman’s pregnancy, as well as rule out ectopic pregnancy, which is life-threatening. The difference in size of an 8-week-old and 12-week-old preborn child is significant”

CONCLUSION

I have a personal interest in this because I had an unwed daughter who became pregnant and started bleeding without telling me because of embarrassment.

She went to a local ER where the doctors said she was just having a miscarriage and sent her home.

When the pain and bleeding increased, she called me. I took her back to the ER to demand an ultrasound.

As I suspected as a nurse, her pregnancy was ectopic and emergency surgery was performed.

Afterward, the surgeon showed me the picture he had taken (unasked) during the surgery to remove the then-deceased first-trimester baby, my grandchild. The picture was personally so sad to see but I was comforted that the surgeon cared enough to take a picture of this tiny person and show respect.

We need more respect and help for women with an unexpected pregnancy and their babies than a pill without medical safeguards!

        “New Study: Brain-injured patients who died after life support ended may have recovered”

        Over the years, I’ve written about several of my patients like “Mike”, “Jack”, Katie” and “Chris” in comas or “persistent vegetative states” who regained full or some consciousness with verbal and physical stimulation. I have also recommended Jane Hoyt’s wonderful 1994 pamphlet “A Gentle Approach-Interacting with a Person who is Semi-Conscious  or Presumed in Coma” to help families and others stimulate consciousness. Personally, I have only seen one person who did not improve much from the so-called “vegetative” state during the approximately two years I saw him weekly.

        Since then, I have written several blogs on unexpected recoveries from severe brain injuries, most recently the 2018 blog “Medical Experts Now Agree that Severely Brain-injured Patients are Often Misdiagnosed and May Recover” and my 2020 blog “Surprising New Test for Predicting Recovery after Coma.

        Now, there is an important new study “New Study: Brain-injured patients who died after life support ended may have recovered”

        As the article states:

        “Using data gathered over a 7 1/2-year period on 1,392 traumatic brain injury patients in intensive care units at 18 U.S. trauma centers, the researchers designed a mathematical model to calculate the likelihood that life-sustaining treatment would be discontinued. They based their model on demographics, socioeconomic factors and injury characteristics.

        Then, they paired patients continuing on life-sustaining treatment to individuals with similar model scores, but for whom life-sustaining treatment was stopped.

        Based on follow-up, the estimated six-month outcomes for a significant proportion of the withdrawn group were either death or recovery of at least some independence in daily activities. Of the survivors in the not-withdrawn group, more than 40% recovered at least some independence.” (All emphasis added)”

        and

        “While many people recover consciousness over a few hours or a day, others remain in the intensive care unit, relying on life support, such as a breathing tube, said Bodien, who also is an assistant professor in the department of physical medicine and rehabilitation at Spaulding Rehabilitation Hospital in Charlestown, Mass.

        “Predicting who will recover following severe traumatic brain injury, and to what degree, can be challenging. Yet, families are often asked to make decisions about continuing or withdrawing life support, such as mechanical breathing, within just 72 hours of the injury,” Bodien said.

        “This decision is based largely on whether the clinical team believes that recovery is possible,” she added. “It is unknown whether some people who died because life support was discontinued could have survived and recovered had life support been continued.”

        Currently, no medical guidelines or precise algorithms determine which patients with severe traumatic brain injury are likely to recover. The most common reason families opt for withdrawing life support measures is physicians relaying information that suggests a poor neurologic prognosis.“

        And:

        “In the study, researchers found that some patients for whom life support was withdrawn may have survived and recovered some independence a few months after injury. Postponing decisions on withdrawing life support may be helpful for some patients, they noted.” (All emphasis added)

        ADVOCATING FOR BRAIN-INJURED PATIENTS

        I personally know how important and often difficult it is for healthcare professionals like myself as well as families when doctors recommend withdrawing treatments on a comatose patient.

        For example and many years ago, I received a phone call from a distraught fellow nurse living in California. Her sister, “Rose”, was comatose from complications of diabetes and had been in an intensive care unit for three days. Now the doctors were telling the family that Rose’s organs were failing and that she had no chance to survive. The doctors recommended that the ventilator and other treatments be stopped so that she could be “allowed to die”. My nurse friend was uncomfortable with the speed of this recommendation even though the rest of the family was ready to go along with the doctors.

        As I told her, back when I was a new nurse in the late 1960s, we would sometimes see patients in the intensive care unit who seemed hopeless and we would speak to families about Do Not Resuscitate (DNR) orders. However, the one thing we didn’t do was to quickly recommend withdrawal of treatment. We gave people the gift of time and only recommended withdrawing treatment that clearly was not helping the person. Some patients did indeed eventually die but we were surprised and humbled when an unexpected number of these “hopeless” patients went on to recover, sometimes completely.

        About six weeks after the initial phone call, my nurse friend called back to tell me that the family decided not to withdraw treatment as the doctors recommended and that her sister not only defied the doctors’ prediction of certain death but was now back at work. I asked her what the doctors had to say about all this and she said the doctors termed Rose’s case “a miracle”.

        “In other words” she noted wryly, “these docs unfortunately didn’t learn a thing.”

        CONCLUSION

        In 1983, I personally dealt with a withdrawal of treatment situation like this in my own family when my baby daughter with Down Syndrome and a severe heart defect developed pneumonia was placed on a ventilator. She was unresponsive and critically ill.

        We hoped to get her stable enough for her planned heart surgery.

        One day, a young resident came in and suggested “getting this over with” by removing her ventilator and “letting her die”. I told him that I would sue if he tried.

        I went to the chairman of pediatric cardiology whom I knew well and told him what happened and the chairman said he would fire him. Instead, I suggested that he try to educate the young doctor first but, if he didn’t get the point, then he should be fired.

        Karen did eventually die in the ICU on the ventilator but I was comforted by the fact that her death was not unnecessarily hastened as well as the fact that later, this wonderful chairman started the first clinic for people with Down Syndrome in the US to deal with their health issues.

        This important study should be mandatory reading for all healthcare professionals and families who need to know the facts.

        Pro-Life and Other Resources for Help and Information to Protect Human Life

        There are many pro-life organizations that can help you or someone you are trying to help find information, referrals and/or other help with crucial decisions about vulnerable lives from conception to death. Here are many of them.

        I am personally on the board of two of these organizations: HALO (Healthcare Advocacy and Leadership Organization) and National Association of Pro-life Nurses (NAPN) and have personally worked with many of the organizations on this list.

        NATIONAL PRO-LIFE ORGANIZATIONS

        The National Right to Life (NRLC) was formed in 1968 and is the largest and oldest pro-life organization in the United States. The mission of NRLC is “to protect and defend the most fundamental right of humankind, the right to life of every innocent human being from the beginning of life to natural death.” They have over 3,000 local chapters, which can be found in all 50 states.

        American United for Life -“We strive for the day when all are welcomed throughout life and protected in law.”

        American Life League-“Building a Culture of Life”

        Charlotte Lozier Institute-“America’s #1 source for science, data, and medical research on the value of human life.”

        Students for Life– “Impacting Campuses & Communities”

        PRO-LIFE SITE TO HELP BOTH PATIENTS AND FAMILIES NAVIGATE THE HEALTHCARE SYSTEM

        HALO (Healthcare Advocacy and Leadership Organization) -“Defending the lives and safety of persons facing the grave consequences of healthcare rationing and unethical practices, especially those at risk of euthanasia and assisted suicide.”

        Please visit the Resources section that includes crucial information about “living wills”, ventilators, etc. and “is designed to help YOU navigate the complicated and sometimes perilous healthcare system. “

        PRENANCY RESOURCE CENTERS

        Carenet-“Acknowledging that every human life begins at conception and is worthy of protection, Care Net offers compassion, hope, and help to anyone considering abortion by presenting them with realistic alternatives and Christ-centered support through our life-affirming network of pregnancy centers, churches, organizations, and individuals. “

        Birthright-“Birthright is a non-profit charitable organization that has been providing love and support for over 50 years to women facing unplanned pregnancies” and offers “free non-judgmental support 24/7

        Abortion Pill Reversal-“Have you taken the first dose of the abortion pill? Do you regret your decision and wish you could reverse the effects of the abortion pill? We’re here for you!” ” Call our 24/7 Helpline: 1-877-558-0333″

        Perinatal Hospice & Palliative Care-Continuing Your Pregnancy -“When Your Baby’s Life Is Expected to Be Brief “

        PRO-LIFE MEDICAL AND NURSING ORGANIZATIONS

        American Association of Pro-Life Obstetricians and Gynecologists  ~   Its membership is 85% OB/GYNS, about 15% Family Medicine, ER and other physicians who deal with reproductive health. It includes midwives, nurse practitioners, etc. who also deal with reproductive health, including pregnancy care center organizations. Membership helps to keep them abreast of what is happening in reproductive health.

        American College of Pediatricians  –  “Pediatricians and Family Medicine physicians who deal in pediatrics, as well as other medical professionals who work in pediatrics.”

        Association of American Physicians and Surgeons  -“Physicians of all specialties.”

        “Christian Medical and Dental Society  -“Christian physicians of any denomination, and Advanced Practice Clinicians of all specialties.”

        National Association of Pro-life Nurses (NAPN)-We care for all lives from conception to the end of life. I encourage all nurses to join and every pro-life person to also visit our Facebook page for more news.

        PRO-LIFE GROUPS FOR HELP AFTER ABORTION

        Project Rachel – “It’s normal to grieve a pregnancy loss, including the loss of a child by abortion. It can form a hole in one’s heart, a hole so deep that sometimes it seems nothing can fill the emptiness. You are not alone.”

        Project Joseph (St. Louis)-“Project Joseph – “a men’s only program through our Abortion Healing Ministry, provides healing and hope to men wounded by abortion.”      

         Elliott Institute was founded in 1988 by Dr. David Reardon, who conducts scientific, evidence-based research on abortion’s effects on women, men, families, and societies. They invest in research, education, and outreach. They are also dedicated to advocacy for women traumatized by abortion and how to provide healing support.

        In addition, the Elliott Institute raises awareness about the injustices of coerced and forced abortions, referring to abortion as the “unchoice.”

        HELP FOR PEOPLE CONSIDERING SUICIDE

        988 Suicide & Crisis Lifeline-“The 988 Lifeline is a national network of local crisis centers that provides free and confidential emotional support to people in suicidal crisis or emotional distress 24 hours a day, 7 days a week in the United States. We’re committed to improving crisis services and advancing suicide prevention by empowering individuals, advancing professional best practices, and building awareness.”

        PRO-LIFE LEGAL GROUPS:

        “Center Against Forced Abortions – The Justice Foundation
        The Justice Foundation’s “Center Against Forced Abortions” or “CAFA”- “was created to provide educational resources to empower women who are being forced, unduly pressured, or coerced into an unwanted abortion.”

        Life Legal Defense Foundation-“Our mission is to give innocent and helpless human beings of any age, particularly babies in the womb, a trained and committed defense against the threat of death, and to support their advocates in the nation’s courtrooms.”

        The Alliance Defending Freedom– “ADF is the world’s largest legal organization committed to protecting religious freedom, free speech, the sanctity of life, marriage and family, and parental rights.”

        Thomas More Society – “For decades, we’ve passionately championed the causes of everyday individuals confronting remarkable injustices, from the sidewalks and town squares to the Supreme Court.”

        American Center for Law and Justice-“Led by Chief Counsel Jay Sekulow, the ACLJ focuses on constitutional and human rights law worldwide. Based in Washington, D.C., with affiliated offices in Israel, Russia, Kenya, France, Pakistan, and Zimbabwe, the ACLJ is pro-life and dedicated to the ideal that religious freedom and freedom of speech are inalienable, God-given rights for all people. The ACLJ engages legal, legislative, and cultural issues by implementing an effective strategy of advocacy, education, and litigation that includes representing clients before the Supreme Court of the United States and international tribunals around the globe.”

        DISABILITY GROUPS (some not formally against abortion)

        The National Down Syndrome Congress on abortion-“National Down Syndrome Congress (NDSC) has long held that abortion for the sole reason that a fetus has Down syndrome borders on eugenics...We believe a better approach is to require healthcare providers to provide their patients with accurate, up-to-date information about the
        realities of having Down syndrome in contemporary America; and, to promote full, meaningful inclusion of all people – with and without disabilities – in every aspect of society.” (Emphasis added)

        National Down Syndrome Adoption Network-“Our mission is to ensure that every child born with Down syndrome has the opportunity to grow up in a loving family.”

        Prenatal Partners for Life-“We are a group of concerned parents, medical professionals, legal professionals and clergy whose aim is to support, inform and encourage expectant or new parents with a special needs child.”

        Simon’s Law -“Simon’s Law says, “NO! No child’s medical chart should have a do not resuscitate order (DNR) and/or the withholding of life sustaining treatments without parental knowledge or consent…No child should be denied life sustaining treatment withheld by a medical professional or insurance provider. Our intent is to make each state a “Simon State” by stopping secret do not resuscitate (DNR) orders!”

        Not dead Yet -“is “a national, grassroots disability rights group that opposes legalization of assisted suicide and euthanasia as deadly forms of discrimination.” (Emphasis added)

        What Will It Take? Part Two -Does Abortion Really Help Women?

        In August 2019, I wrote a blog titled “Pro-abortion Desperation in Missouri” about the last Planned Parenthood abortion clinic in Missouri losing its license because of numerous health and safety violations but continued to operate only because of several temporary injunctions by a judge.

        The clinic finally closed only after the Supreme Court’s June 2022 Dobbs v. Jackson Women’s Health Organization decision returned abortion law to the states.

        Unfortunately, the pro-abortion choice response to that decision has resulted in terrible turmoil and animosity.

        Now the attacks on pro-life pregnancy centers and churches with few arrests and prosecution of peaceful pro-life demonstrators are continuing unabated.

        To try to portray abortion as a positive empowerment for women, Planned Parenthood has tried the “Share Your Story” and “Shout Your Abortion— Normalizing abortion and elevating safe paths to access, regardless of legality” campaigns to increase abortion support and activism. (The National Association of Pro-life Nurses countered with “Shout out Your Adoption!“, pointing out that “Adoption is a wonderful act of love and one of the best alternatives to abortion.”)

        Now Planned Parenthood has another strategy for increasing abortion support and activism originally published in MS Magazine on 4/12/2022 and titled “A Firsthand View of the Crisis Ahead for Abortion Rights—and What We Should Do About It”

        The article states:

        “Since it seems we can no longer rely on the courts to protect these rights, our only solution is to pass a new federal law that will protect abortion rights in all 50 states. The Senate’s recent failure to pass the Women’s Health Protection Act makes it clear that we will need a greater pro-choice majority than we have today to pass this new legislation.

        This will not happen in one election cycle, and it will take a commitment of time, energy and resources beyond that which we have been expending to date. We have to get all the voters who support reproductive rights registered and encourage them to vote. We have to elect representatives at all levels of government who will protect our reproductive rights that are currently under attack. (Emphasis in original)

        THE TRAUMA OF ABORTION

        And as a nurse, I have seen the mental and/or physical trauma after abortion in both friends and patients.

        For example, one friend felt she had to have an abortion because the doctor said her unborn baby had little or no brain, which may not have even been true according to the doctor I knew who read the ultrasound. That doctor was devastated to learn that an abortion was done.

        Knowing that I was pro-life, my friend said she didn’t want to talk about the traumatic 28 hour induced abortion but, after 5 years, she called me and said she needed to know how the hospital disposed of the body. She also revealed that she secretly hung an ornament for that baby on the Christmas tree every year.

        And I wrote a November 2016 blog “Why Talk About Abortion” about one of my elderly hospice patients who told me that she was afraid to die because of a secret abortion she had 60 years ago because she believed that abortion was an “unforgivable sin” and she would go to hell. She also felt her now swollen belly due to her terminal condition was God punishing her for the abortion.

        My heart went out to this woman who was suffering so much, more emotionally than even physically.

        We talked for a long time and in a later visit about God’s love and forgiveness. I told her about Project Rachel, a healing ministry for women (and even men) wounded by abortion. I gave her the phone number and offered to be with her to meet a counselor or priest, but she insisted that my talking with her was enough to help. I felt it wasn’t, but she seemed to achieve a level of peace and she even started smiling! 

        Rose died comfortably and apparently in her sleep about a week later.

        SOME RESOURCES TO HELP WOMEN WHO ARE CONSIDERING ABORTION OR OTHERS WHO ARE HURTING AFTER AN ABORTION

        1. Support After Abortion “aspires to shift the conversation to compassion and support for those impacted by abortion” (including men)
        2. Project Rachel for women and even including how to talk to a friend who has had an abortion
        3. Birthright An organization with many resources and help
        4.  American Association of Pro-Life Obstetricians and Gynecologists states it “Promotes Dignity for BOTH our Patients!”
        5. There are also organizations like Prenatal Partners for Life and Be Not Afraid that provide support, information, resources and encouragement for carrying to term with an adverse prenatal diagnosis.

        6. CareNet helps find a crisis pregnancy center in your area

        CONCLUSION

        Serrin M. Foster of Feminists for Life in her 2018 National Review article “Women Deserve Better than Abortion: The Ultimate Exploitation of Women” perhaps said it best:

         “The reality is that there is no such thing as a safe abortion. Few unborn human beings escape a violent death, but what is underreported is the mortality of healthy pregnant women killed during or as a result of abortion.

        When we know how much a woman grieves from reproductive loss through miscarriage or stillbirth, who would choose abortion? According to the Guttmacher Institute, those who have abortions come primarily from the poorest among us (75 percent), women of color (61 percent), women pursuing post-secondary degrees that would lift them out of poverty (66 percent), and mothers who already have dependents (59 percent). Half of all abortions are performed on a woman who has already had one or more abortions, proving that abortion solves nothing. Abortion isn’t empowering, and it’s not something to celebrate. Abortion is a symptom of, not a solution to, the problems faced overwhelmingly by women who don’t have what they need and deserve. Abortion is a reflection that we have not met the needs of women. Women deserve better.”

        And ALL of us deserve a better and more peaceful society!

        WHILE PRO-ABORTION VIOLENCE AGAINST PRO-LIFE CRISIS PREGNANCY CENTERS INCREASES, THE WORLD HEALTH ORGANIZATION SAYS CONSCIENCE RIGHTS REGARDING ABORTION MAY BECOME “INDEFENSIBLE”

        We have been witnessing the rage and misinformation dividing Americans after the outrageous leak of Supreme Court Justice Alito’s draft decision on the Dobbs v Jackson Women’s Health Organization returning abortion laws back to the states since it was reported on May 2, 2022.

        Many pro-life crisis pregnancy centers are now being attacked with paint, firebombs, etc. by pro-abortion groups like “Jane’s Revenge”. But as Nicole Ault of the Wall Street Journal points out:

        “No woman is forced to go to one of these clinics, where more than 10,000 licensed medical professionals worked or volunteered as of 2019, according to the pro-life Charlotte Lozier Institute. In addition to providing ultrasounds and pregnancy tests, the centers help women get supplies and counseling.”

        But then, on June 8, 2022 and during the night, U.S. Marshals protecting the home of Supreme Court Justice Brett Kavanaugh from illegally picketing protesters apprehended an individual with a gun and a knife who readily admitted that “he was there to kill Justice Kavanaugh in response to the leaked draft opinion that indicated the Court might be preparing to overturn Roe v. Wade.”

        Now, Jane’s Revenge has issued a call to ‘riot’ against the Supreme Court if it does overturn Roe v. Wade.

        Their flyer “DC CALL TO ACTION NIGHT OF RAGE” declares “THE NIGHT SCOTUS OVERTURNS ROE V. WADE HIT THE STREETS YOU SAID YOU’D RIOT. TO OUR OPPRESSORS: IF ABORTIONS AREN’T SAFE, YOU’RE NOT EITHER.’ JANE’S REVENGE.” (Emphasis added)

        THE WORLD HEALTH ORGANIZATION ON ABORTION

        On March 8, 2022, the World Health Organization (WHO), the international body responsible for public health and part of the United Nations involved in many aspects of health policy and planning, issued its’ “Abortion Care Guideline“.

        In the Guideline, WHO recommends “the full decriminalization of abortion” and calls conscientious objection to abortion a major obstacle to making abortion freely available.

        According to the WHO recommendations:

        “If it proves impossible to regulate conscientious objection in a way that respects, protects and fulfils abortion seekers’ rights, conscientious objection in abortion provision may become indefensible.” (Emphasis added)

        CONCLUSION

        Personally, when my daughter Karen, born with Down Syndrome and a severe heart defect, died at 5 1/2 months in 1983, my grief was substantially lessened by donating Karen’s clothes, formula, etc. to our local Birthright organization, one of the many pro-life organizations providing help to pregnant women.

        Since Karen and as a nurse and mother, I have been able to help advocate for distressed mothers and their families, children and adults with disabilities and, best of all, my own daughter who found she was pregnant in her first year of college and gave birth to my first grandchild.

        And I know that the WHO is absolutely wrong in calling conscientious objections to abortion “indefensible”. Conscience rights are critically important for all of us, whether or not we are healthcare providers.

        As I wrote in my December 13, 2019 blog “Are We Witnessing the Coming Extinction of Conscience Rights?”:

        “With the current support of a predominantly sympathetic mainstream media, well-funded and politically active groups like Planned Parenthood and Compassion&Choices are also putting pro-life health care providers and their supportive institutions in grave danger of becoming an endangered species in law, politics and health care.

        If this happens, our health care system will radically change-especially for the unborn, the elderly and people with disabilities.

        When dedicated and compassionate people are denied entry into the health care professions because they refuse to deliberately end lives, harassed and/or fired when they refuse to participate in a deliberate death decision and efforts to make religiously based healthcare institutions to allow lives to be ended by “choice”, will any of us ever be able to trust our healthcare system when we need it the most?” (Emphasis added)

        Rest in Peace, “Melissa”

        I have written blogs about my elderly friend “Melissa” (not her real name) and some of her health care experiences to explain some of the pitfalls elderly people may encounter when they get seriously ill.

        I have known “Melissa” for decades and, with her permission, she agreed to my writing about her in my blogs. She was thrilled to hear about my 2018 blog “Covid 19 and Nursing Homes”   and my 2020 blog “Don’t Write Off the Elderly”.

        She even told me she like the name “Melissa” better than her real name!

        I first met Melissa when she was in her 80s through her daughter who is also one of my favorite people.

        Both were involved in planning the beautiful wedding reception at my home when my second husband and I were married in 2008. Melissa even remembered my favorite flower and made beautiful centerpieces with them for every table.

        After Melissa could no longer drive, I took her to Mass at her parish and then to Chic-Fil-A on Fridays for breakfast with her daily Mass friends until she couldn’t physically make it.

        I then visited her on Fridays and was inspired when she accepted hospice care and the care of her family with grace and gratitude.

        Eventually, she spent her last days in a bed near a large window where she could watch the birds at her birdfeeder and have some of her beloved flowers at her bedside.

        During that time, Melissa and I laughed a lot, prayed together, chatted about current events and family, and watched funny videos and old episodes of TV shows she enjoyed like “Barney Miller” and “Bewitched”.

        She also told me many of the fascinating stories behind the pictures of her and her family covering the walls of her room.

        Melissa died peacefully on May 6, 2022, at her home at the age of 99 years, 9 months and 5 days, lovingly cared for by her family and great home health and hospice providers.

        A devout Catholic, Melissa was unafraid of death and knew she would meet her late husband and her son who died at age 4. Another son unexpectedly died at 56, shortly before Melissa.

        Melissa generously donated her body to Logan College to help future doctors with their education.

        After her funeral Mass, her family had a Celebration of Life event with pictures and stories about her life. There was a lot of laughter and some tears as we all talked about Melissa and what she meant to us.

        CONCLUSION

        Melissa and her family are an inspiration to me and an example of how to have a good death, something that seems impossible to many people.

        I visited her the day she died peacefully and comfortably, but not awake.

        She died just as she hoped.

        We will miss you Melissa but we will never forget you!

        Rest in peace.